Hair changes after 40 rarely come from one cause. Perimenopause, inherited follicle sensitivity, nutritional deficiencies, illness, stress, medication changes and years of styling can overlap. The result may look like “sudden” hair loss, even though the process began months earlier.
For women in Victoria, BC, the first step is not buying another supplement or booking a generic package. Start by identifying whether you are experiencing increased shedding, true thinning, or both.
Medical note: Hair loss can have medical causes. Sudden, patchy or rapidly progressing loss, or loss accompanied by scalp pain, scaling, sores, marked inflammation or systemic symptoms, requires assessment by a physician or dermatologist. AGE LESS Laser+Clinic does not diagnose hair-loss conditions.
Shedding is not the same as thinning
Normal hair growth moves through three main phases:
- Anagen: active growth
- Catagen: a short transition phase
- Telogen: resting and shedding
When many follicles enter the resting phase at the same time, you may notice more hair in the shower, on your pillow or in your brush. This pattern is often called telogen effluvium.
Telogen effluvium typically causes diffuse shedding across the scalp. It may follow a fever, surgery, significant stress, rapid weight loss, restrictive dieting, medication change or hormonal shift. The trigger often occurs two to three months before the shedding becomes obvious, which makes the connection easy to miss.
True thinning follows a different pattern. Female-pattern hair loss, also called androgenetic thinning, usually develops gradually. The central part may widen, the crown may become more visible, and individual hairs may grow finer over time. Shedding and pattern thinning can occur together.
Traction adds another layer. Tight ponytails, extensions, braids, clips and repeated tension can stress the follicles around the hairline and temples. If traction continues, the damage may become more difficult to reverse.
Why perimenopause can change the picture
Oestrogen and progesterone influence the hair-growth environment. As hormone levels fluctuate and decline during perimenopause and menopause, the active growth phase may become less robust for some women. Genetically sensitive follicles may also respond more strongly to androgen signalling, leading to gradual miniaturization.
This does not mean menopause creates one uniform type of hair loss. Hormonal change may be one contributor among several. It can also expose a pattern that was developing quietly for years.
The timing creates confusion. A woman may notice increased shedding in her late 40s, yet the hormonal or metabolic trigger may have started months earlier. Menstrual changes, sleep disruption, stress, altered appetite and changes in body weight may all provide important context.
The first practical step: investigate before treating
A blood panel is not a hair-loss treatment. It is a way to look for correctable contributors.
Depending on your history, a physician may consider:
- Complete blood count
- Ferritin and iron studies
- Thyroid testing, often beginning with TSH
- Vitamin D
- Vitamin B12 or zinc when clinically appropriate
- Hormonal testing when there are irregular periods, new facial hair, severe acne or other signs of androgen excess
Low ferritin may contribute to diffuse shedding, but there is no single hair-specific threshold that applies to every woman. Do not take iron without confirming deficiency and discussing the cause. Excess vitamin A, selenium and biotin can also create problems, including interference with laboratory tests.
Protein matters when intake is inadequate. Severe restriction, crash dieting and rapid weight loss can push more follicles into the shedding phase. Aim for regular meals that include a reliable protein source rather than relying on “hair vitamins” as a substitute for adequate nutrition.
Styling damage matters more in midlife
Hair fibre often becomes finer, drier or more fragile with age. That makes mechanical and chemical stress more visible.
Reduce avoidable damage by:
- Brushing gently, beginning at the ends
- Avoiding aggressive detangling when hair is wet
- Rotating tight hairstyles
- Limiting high heat and using heat protection
- Avoiding repeated harsh colouring or overlapping chemical services
- Choosing a gentle cleanser that suits the scalp rather than over-washing or under-washing
A healthy scalp does not require complicated products. It requires a clean, comfortable environment without persistent irritation, heavy buildup or unnecessary friction.

What actually helps?
Low-level light and laser therapy
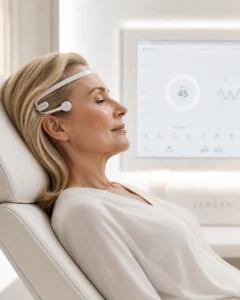
Low-level light therapy, sometimes discussed as photobiomodulation, uses specific wavelengths, treatment doses and schedules. It is not equivalent to using an ordinary red-light bulb at home.
Research suggests that appropriately designed low-level light systems may provide a modest improvement in hair density or shaft diameter for selected people with pattern hair loss. The evidence is less established for every other cause of shedding, and treatment should not delay medical assessment.
Consistency matters. Hair follicles work slowly, so meaningful evaluation generally requires at least three to six months, often longer. A single session cannot show whether a follicle-support plan is working.
Learn more about AGE LESS low-level light therapy for hair restoration.
Minoxidil
Topical minoxidil has some of the strongest routine evidence for female-pattern hair loss. It may help preserve or improve the appearance of existing follicles, but it does not address every cause of shedding and does not restore follicles that are no longer viable.
Possible issues include early increased shedding, scalp irritation and unwanted facial hair. Benefit depends on consistent use, and any improvement generally requires continued use to maintain it. Discuss suitability with a physician or pharmacist, particularly during pregnancy, while trying to conceive or during breastfeeding.
Prescription oral minoxidil may suit selected individuals but requires medical screening and monitoring. It is not appropriate for everyone.
PRP and regenerative scalp options
Platelet-rich plasma, or PRP, may improve density for some people with pattern hair loss. However, studies use different preparation methods, injection schedules and outcome measures. That makes the results difficult to compare.
Treat PRP as an optional adjunct, not a guaranteed replacement for medical therapy. Ask what protocol is being used, how progress will be measured, how many sessions are anticipated and what the total cost will be.
Other regenerative scalp-support options, including targeted micro-infusion approaches, are also being explored and used in clinical settings. Their role depends on the diagnosis, the condition of the scalp and the strength of the available evidence. Regenerative language should never be used to imply guaranteed regrowth.
Why AGE LESS takes a layered approach
AGE LESS Laser+Clinic begins with the pattern, scalp condition, history and relevant lifestyle factors rather than recommending the same package to every Client. The goal is to clarify whether the priority is scalp support, light therapy, medical referral, nutrition review, medication discussion or a combination.
That reflects an inside-out and outside-in philosophy:
- Inside out: review health history, hormones, stress, nutrition and medical factors
- Outside in: support the scalp environment with appropriate cleansing, light-based therapy or selected regenerative options
- Measure over time: use consistent photographs, timelines and realistic checkpoints
This is different from a high-volume clinic model that sells one protocol before understanding the person. Hair needs a plan, not one product.
AGE LESS Laser+Clinic — Trusted by Thousands Since 2000. The clinic has served Clients across the Greater Victoria area, from Saanich, Brentwood Bay and Sidney to downtown and the Westshore, and the wider Southern Vancouver Island and lower Cowichan Valley, for more than two decades, and since 2024 has welcomed them from its boutique clinic in Esquimalt.
A realistic timeline
Hair biology moves slowly. You may notice changes in shedding before you see a visible increase in density, but meaningful assessment usually takes three to six months. A fuller evaluation of pattern and response may require six to twelve months.
Use the first visit to establish clarity:
- Record when the change began.
- Note illness, stress, weight loss, dietary restriction or medication changes.
- Photograph the part, hairline and crown in consistent lighting.
- Arrange medical assessment when symptoms or red flags warrant it.
- Choose only those interventions that match the likely cause.
If you are searching for hair loss prevention in Victoria, BC or hair loss treatment in Victoria, BC, begin with evidence, not urgency. A careful assessment will not promise a result, but it can prevent months of unsuitable products and help you choose the next step with far greater confidence.
This article is educational and does not replace medical advice. Individual causes, suitability, timelines and results vary. Prescription treatments should be discussed with a qualified medical professional.